
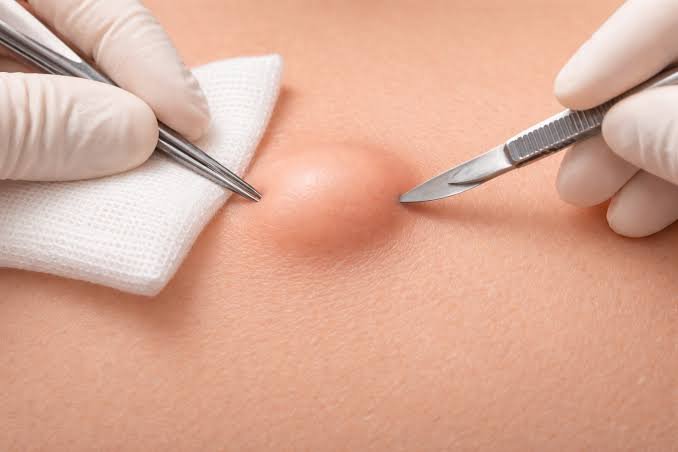
A cyst may look flat after drainage, yet slowly return to the same place. This often happens because drainage releases the trapped material but leaves the cyst wall beneath the skin.
The remaining lining can continue producing keratin, allowing the cavity to fill again. Understanding this difference helps patients choose treatment based on the cyst’s condition and recurrence history.
What Should You Know About a Cyst That Keeps Returning?
Many lumps called sebaceous cysts are actually epidermoid or pilar cysts. A clinician can assess the lump, explain whether it appears cystic, and discuss whether drainage, monitoring, or complete removal may be suitable.
Before deciding what to do, consider these practical points:
- How long the lump has been present
- Whether it has returned after previous drainage
- How quickly it refills
- Whether it becomes painful or swollen
- Whether redness, heat, or discharge develops
- Whether the lump feels firm or fixed
- Whether it interferes with clothing or movement
- Whether the diagnosis has been medically confirmed
The table below explains why different approaches can lead to different outcomes.
| Approach | What It Does | Chance of Refilling |
| Observation | Leaves the cyst untouched while monitoring changes | The cyst may remain stable or enlarge |
| Simple drainage | Releases the cyst contents through an opening | Refilling is possible because the lining remains |
| Treatment during inflammation | Controls pain, pressure, or infection first | Definitive removal may still be needed later |
| Complete excision | Removes the contents and cyst wall | Recurrence is less likely, but still possible |
| Laboratory examination | Confirms the nature of removed tissue | Does not prevent recurrence but supports diagnosis |
Why Can a Drained Cyst Fill Up Again?
Drainage and complete removal are not the same procedure. Drainage deals with what is inside the cyst at that moment, while excision aims to remove the structure that allows the material to collect.
The Cyst Wall Remains Under the Skin
A cyst is not simply a pocket of liquid. It usually has a lining that forms a closed sac beneath the skin and continues producing material after the contents are released.
If that lining remains, the source of the cyst remains too. The sac can gradually collect more keratin and become noticeable again weeks, months, or even years later.
The Contents Are Keratin Rather Than Oil
The term sebaceous cyst is widely used, but many of these lumps are epidermoid cysts. They commonly contain keratin, a protein found in skin, hair, and nails.
The material may look thick, pale, and paste-like. Keratin builds up inside the sac as lining cells shed, which explains why the lump can refill after drainage.
A Small Opening Does Not Remove the Sac
Drainage normally uses a small opening to release pressure and remove some of the contents. That opening may close while the deeper lining remains in its original position.
The surface can therefore appear healed even though the cyst structure is still present. Once the opening seals, newly produced material has nowhere to escape.
Inflamed Tissue Is Harder to Remove Completely
An inflamed cyst can become swollen, painful, and attached to nearby tissue. Its wall may also become fragile, making clean separation more difficult during an active flare.
A clinician may first manage inflammation or infection before considering sebaceous cyst assessment and removal. Timing can influence complete removal and wound management.
Part of the Capsule May Be Left Behind
Even during planned excision, a thin section of the cyst wall may occasionally remain. This is more likely when the lining has ruptured, scarred, or become difficult to distinguish.
Remaining lining cells can form another pocket over time. Careful removal of the capsule helps reduce recurrence, although no procedure can promise that a cyst will never return.
Previous Rupture Can Cause Scarring
A cyst may rupture beneath the skin before treatment. Escaped keratin can trigger inflammation because the body reacts to it as material that should not be in surrounding tissue.
Inflammation may create adhesions and scar tissue around the sac. Scarring can blur the cyst boundary, making later removal more involved than excision of a calm, intact cyst.
The Lump May Have Been Misidentified
Not every rounded skin lump is a cyst. Lipomas, abscesses, enlarged lymph nodes, and other growths can sometimes have a similar appearance without being the same condition.
Repeated treatment without a clear diagnosis may not solve the problem. Clinical assessment matters, particularly when a lump is firm, fixed, rapidly growing, unusually painful, or changing in appearance.
How Can Recurring Cysts Be Managed More Effectively?
The right approach depends on the diagnosis, symptoms, inflammation, location, health history, and personal preference. A clinician should examine the area before recommending another drainage procedure or excision.
1. Allow Active Inflammation to Settle
Removing an inflamed cyst can be harder because the tissue is swollen and the capsule may tear easily. In some cases, treatment is staged instead of completed in one appointment.
The first priority may be reducing pressure or treating infection. Definitive removal can follow later when the area is calmer and the cyst boundary is easier to identify.
2. Consider Complete Surgical Excision
Complete excision aims to remove both the cyst contents and its lining. This addresses the sac that produces and collects keratin rather than only emptying it.
A clinician will consider the cyst’s size, position, and previous treatment. Removing the entire cyst wall generally offers a lower chance of recurrence than drainage alone.
3. Discuss the Expected Scar
Cyst removal requires an opening in the skin, so a scar should be expected. Its final appearance depends on incision length, wound tension, location, healing, and individual skin behaviour.
A small opening may sound appealing, but access must be sufficient for safe removal. Balanced incision planning considers both capsule removal and the likely cosmetic result.
4. Avoid Squeezing the Cyst at Home
Pressing a cyst may force material deeper into nearby tissue rather than clearing the sac. It can also cause rupture, bleeding, inflammation, infection, and further scarring.
Home squeezing does not remove the cyst lining. Repeated manipulation can complicate treatment and may make the area more painful or difficult to assess later.
5. Follow Wound Care Instructions
After removal, the wound may need a dressing, stitches, or activity restrictions. Patients should follow advice on washing, exercise, pain relief, and returning for suture removal.
Good care supports healing but cannot correct incomplete excision. Protecting the healing wound reduces avoidable irritation and helps the clinical team identify problems promptly.
6. Attend Any Recommended Follow Up
Follow up allows the clinician to inspect the wound, review healing, and discuss laboratory findings if tissue was sent for examination. It also gives patients time to raise concerns.
A returning swelling should not be ignored or assumed to be harmless. Early reassessment is useful when the area becomes painful, begins discharging, or develops a new lump.
7. Ask Whether Tissue Will Be Examined
Removed tissue may be sent to a laboratory to confirm the diagnosis. This can be valuable when the cyst looks unusual, has returned repeatedly, or was difficult to separate.
Histology does not prevent the cyst from returning, but it provides diagnostic confirmation. The result can guide further care if the tissue is not what was initially expected.
When Should a Recurring Lump Be Reviewed Promptly?
The NHS advises seeking medical assessment for unexplained lumps rather than diagnosing them at home. Prompt review is particularly important when the lump behaves differently from a typical slow growing cyst.
Contact a qualified medical professional if the lump:
- Grows quickly or changes noticeably
- Becomes hard, fixed, or irregular
- Feels increasingly painful
- Develops spreading redness or heat
- Produces pus or persistent discharge
- Returns repeatedly after treatment
- Causes fever or general illness
- Affects movement, sensation, or daily comfort
- Bleeds or develops an open wound
- Has never received a confirmed diagnosis
Conclusion
A drained cyst often refills because its lining remains beneath the skin and continues producing keratin. Drainage can ease pressure, but it does not always provide a lasting solution. Complete excision may reduce recurrence when clinically suitable. Any lump that grows quickly, becomes hard or painful, repeatedly returns, or causes infection should be assessed by a qualified medical professional.

